Most tesamorelin data comes from men. If you're looking into tesamorelin for women, mostly for stubborn belly fat, that's the first thing to know: in the two trials that got it approved, about 15 in every 100 people were women, and all of them had HIV. This guide pulls out what those trials, and the handful of smaller ones since, actually showed for women, what the current label says about dose and pregnancy, and where the evidence simply runs out.
🔑 Key Takeaways
- It targets the fat around your organs, not the fat you can pinch, and the scale barely moves
- The only trial in people without HIV left out every woman past menopause
- Where results were checked by sex, women and men responded about the same
- Birth control pills and oral HRT may change how your IGF-1 levels read
- Pregnancy is a hard no on the label, and the reason is spelled out
Every number below links to the trial paper or the FDA label it came from, listed at the end. Where a question has no human data, we say so rather than fill the gap.
Tesamorelin for Women: What It Is Approved For
It has one approved use, and it's narrow. Tesamorelin (brand names Egrifta SV and Egrifta WR) is approved to reduce excess abdominal fat in adults with HIV who have lipodystrophy. The FDA label applies to women and men alike, and it adds two limits worth reading twice: it is "not indicated for weight loss management as it has a weight neutral effect," and its long-term heart safety hasn't been established.
It works upstream of growth hormone. Tesamorelin is a copy of the brain's growth hormone-releasing hormone (GHRH), so it prompts your pituitary to release more of your own growth hormone, which raises IGF-1 and shrinks visceral fat. For the full background on how it works, see our tesamorelin peptide guide. Everything below is about what changes when the person taking it is a woman.
How Many Women Were in the Tesamorelin Trials?
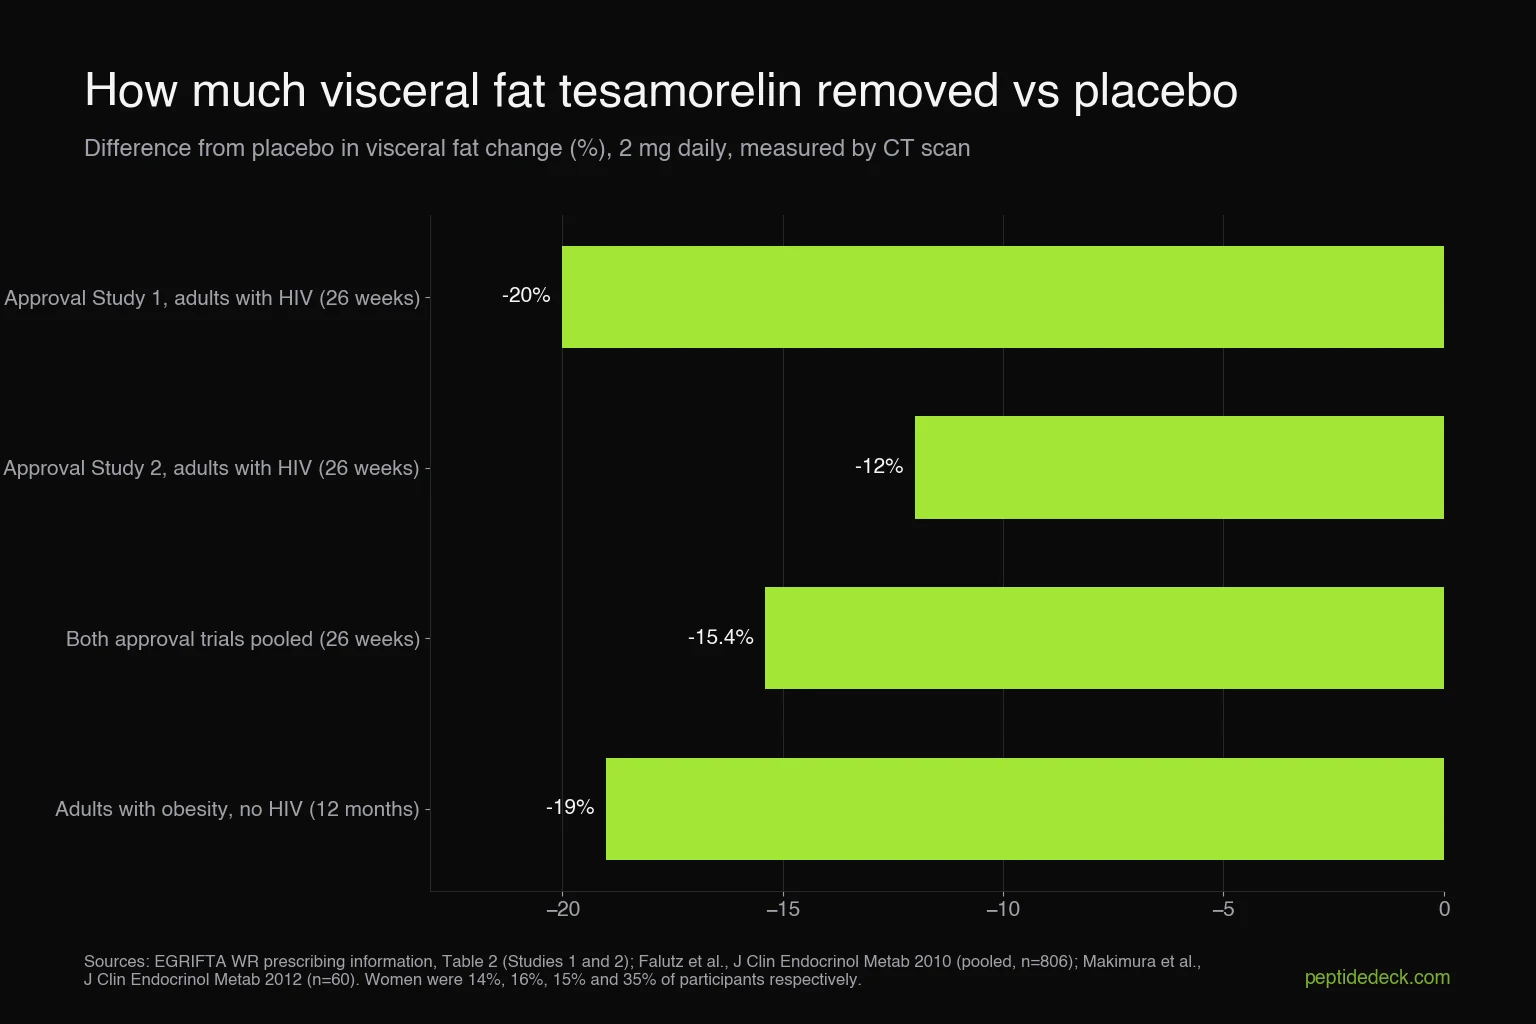
Fewer than you'd expect from the marketing. The label reports that Study 1 was 86% men and Study 2 was 84% men. A 2026 meta-analysis that tabulated both arms puts the total at 121 women out of 806 randomised, all with HIV.
The trial rules also shaped which women got in. To qualify, women needed a waist of at least 94 cm (37 inches) and a waist-to-hip ratio of at least 0.88. They needed a normal mammogram, couldn't be pregnant, and, as the trial methods list it, couldn't be on estrogen therapy. So women on HRT were not studied in the trials that led to approval.
Here is every trial we could open that enrolled women and reported how many.
One trial stands out for women without HIV: Makimura and colleagues gave 2 mg a day for a year to 60 adults with abdominal obesity and low growth hormone output. It's the closest thing to the person reading this page. But look at the exclusions: anyone over 55, any woman with an FSH above 20 (a marker of menopause), and anyone on estrogen, HRT or the pill. The 21 women in it were premenopausal and hormone-free.
We searched PubMed and ClinicalTrials.gov on November 5, 2026, and found no tesamorelin trial that enrolled only women, and none in menopausal women without HIV.
Did Women Respond Differently From Men?
Where anyone checked, the answer was no. Three sources looked at sex directly.
- Visceral fat. In the obesity trial, the drop in visceral fat stayed significant after adjusting for sex, "without any gender effect seen in the model."
- IGF-1 and body fat. In Baker's trial of 152 older adults (59% women), the IGF-1 rise did not differ by sex (P = 0.69), and the 7.4% drop in body fat was similar in women and men.
- How the body handles the drug. A pharmacology analysis of 41 people found no effect of sex on growth hormone or IGF-1 responses.
There's one difference worth noticing. In Baker's trial, women reported side effects more often than men, and 11 of the 13 people who needed a dose reduction were women. That trial used 1 mg a night, half the approval-trial dose.
The limitation: none of these trials was designed or sized to compare women with men. "No difference found" in groups of 10 to 90 women is not the same as proof that women respond identically. The authors of a sponsor-funded analysis of the two approval trials said their findings "may not apply to other ethnicities or to women."
Tesamorelin Benefits for Women: What's Realistic
The benefit is specific, and so is its limit. In the pooled approval trials, visceral fat (the deep fat around the organs) fell while the fat under the skin of the belly barely changed: a −0.6% treatment effect, according to the pooled analysis.
Here's what that looks like in daily life, based on the label and trial data:
- Your weight may not change. Weight moved by less than half a kilo against placebo in both approval trials.
- Your waist may shrink a little. Waist circumference fell by 1 to 2 cm more than placebo over 26 weeks.
- Triglycerides tend to drop. The pooled treatment effect was −12.3%.
- Liver fat can fall. In the fatty-liver trial, 35% of people on tesamorelin reached a normal liver fat level, against 4% on placebo.
- How people felt about their belly improved. Belly-appearance distress scores improved compared with placebo.
The gains don't last after stopping. In the second approval trial, people switched from tesamorelin to placebo lost the visceral-fat improvement "rapidly," according to Falutz and colleagues. If what you want is weight on the scale coming down, a GLP-1-type drug does a different job. Our tesamorelin vs retatrutide comparison covers that trade-off.
Menopause, Belly Fat and Tesamorelin
Menopause does move fat inward. In the SWAN study of 380 women followed for a median of nearly 12 years, visceral fat began rising at the menopause transition, by about 6.2% a year in the study's reference group, and kept rising more slowly after. In a smaller 4-year study of 156 women, only the women who became postmenopausal gained visceral fat; all of them gained fat under the skin.
So the logic for a visceral-fat drug at midlife is easy to follow. The trial data isn't there yet. The non-HIV obesity trial excluded postmenopausal women. The 2014 JAMA trial included six postmenopausal women, far too few to say anything about them on their own. If menopause is your reason for asking, our guide to peptides for menopause covers what has been tested for hot flashes, sleep and body composition.
The Pill, Oral HRT and Your IGF-1 Levels
How you take estrogen matters here. Oral estrogen passes through the liver first, and the liver makes most of the IGF-1 in your blood.
- In postmenopausal women, oral ethinyl estradiol lowered IGF-1 (from 0.70 to 0.47 U/mL) over two months, while a transdermal estradiol patch raised it.
- In eight women with growth hormone deficiency, oral estrogen blunted the IGF-1 rise from growth hormone injections compared with a patch.
- In a clinic review of 88 women on growth hormone, those on ethinyl estradiol birth control pills needed higher doses and responded less.
None of these studies used tesamorelin. Because tesamorelin acts through your own growth hormone, the same effect is plausible, but it hasn't been tested. The approval trials excluded estrogen therapy, and the obesity trial excluded HRT and the pill. Baker's trial allowed estrogen (17 users), but didn't report their results separately.
Why it matters to you: IGF-1 is the blood test used to monitor tesamorelin. If you're on the pill or oral HRT, your doctor should know before reading the number. The label also notes that growth hormone may change how the liver clears sex steroids, so tell your prescriber about every hormone you take.
And PCOS? A PubMed search for tesamorelin and polycystic ovary syndrome returned no studies on November 5, 2026, so there's nothing to report either way.
Tesamorelin Dosage for Women
The label dose is the same for everyone. There's no separate dose for women in either label. Which number applies depends on the product.
- Egrifta WR: 1.28 mg once daily under the skin of the abdomen. The FDA approved this concentrated formulation on March 25, 2025, and the company says it is set to replace Egrifta SV. You mix one vial once a week, not every day.
- Egrifta SV: 1.4 mg once daily (0.35 mL from a 2 mg vial), mixed fresh each day. It's still listed on DailyMed.
- 2 mg once daily was the dose in the approval trials and most later trials, using the original Egrifta formulation. The newer products deliver the same exposure at a lower number of milligrams.
The label says the WR and SV formulations are not substitutable, so the milligram figure only makes sense for the product it belongs to. For the full dosing walk-through, see our tesamorelin dosage guide.
Getting it is the harder part for most women. A prescription for Egrifta is written for HIV-associated lipodystrophy; anything else is off-label, and our guide to how to get tesamorelin explains each route. If you're comparing prices and suppliers, our guide on where to buy tesamorelin covers cost and what to check before paying.
Tesamorelin Side Effects in Women
Most side effects are mild and local. These are the label's figures from the first 26 weeks of the approval trials, for reactions more common on tesamorelin than placebo.
Three label warnings deserve attention:
- IGF-1 can run high. After 26 weeks, 47% of people had IGF-1 above 2 standard deviation scores and 36% above 3. The label says to monitor IGF-1 and consider stopping if it stays high.
- Blood sugar. The risk of reaching an HbA1c of 6.5% was higher on tesamorelin (5% vs 1%). Your glucose should be checked before you start and during treatment.
- Fluid retention. Swelling, joint pain and carpal tunnel symptoms are tied to the growth hormone rise and usually settle or resolve on stopping.
Hypersensitivity reactions such as rash and hives occurred in 4% of people. More detail on managing each one is in our tesamorelin side effects guide.
Pregnancy, Breastfeeding and Other No-Go Situations

Pregnancy is a listed contraindication. The label states tesamorelin is contraindicated in pregnancy "because modifying visceral adipose tissue offers no benefit in pregnant women and could result in fetal harm," and tells women to stop if they become pregnant.
The label says not to use tesamorelin if you:
- are pregnant
- have a disrupted hypothalamic-pituitary axis (pituitary surgery or tumour, hypopituitarism, head radiation or head trauma)
- have an active cancer (any past cancer should be inactive and its treatment complete)
- are allergic to tesamorelin or its ingredients
On breastfeeding, the label tells mothers on tesamorelin not to breastfeed. Part of that is HIV transmission, but the label also cites the risk of serious reactions in nursing infants and notes there is no data on whether tesamorelin gets into breast milk.
Cancer screening matters too. Because growth hormone is a growth factor, the trials required women to have a normal mammogram before enrolling, and the 2019 liver trial required one within a year for women aged 50 or older. If you're due for a screening, have it done first.
What to Ask Your Doctor
Bring these questions to the appointment.
- Is my belly fat mostly visceral? Can we measure it (a DEXA or CT scan), so we know whether it's changing?
- What is my IGF-1 now, and how often will we check it?
- I take the pill or oral HRT. Will that affect my IGF-1 reading or how well this works? Would a patch make a difference?
- Is my HbA1c or fasting glucose high enough that tesamorelin's blood sugar effect is a concern?
- Am I up to date on my mammogram and other cancer screening?
- What's the plan if I want to get pregnant, and how far ahead should I stop?
- If I stop, the visceral fat may come back. What's the long-term plan?
For how tesamorelin compares with a gentler GH-releasing option women often ask about, see sermorelin for men and women.
Frequently Asked Questions
Sources
- EGRIFTA WR (tesamorelin) for injection, prescribing information. Theratechnologies. DailyMed, label version published August 3, 2026. DailyMed
- EGRIFTA SV (tesamorelin) for injection, prescribing information. Theratechnologies. DailyMed, label version published July 31, 2026. DailyMed
- FDA approves F8 formulation of Theratechnologies' tesamorelin for HIV-associated lipodystrophy. Contagion Live, March 25, 2025 (updated April 8, 2025). Contagion Live
- Falutz J, et al. Metabolic effects of a growth hormone-releasing factor in patients with HIV. N Engl J Med. 2007;357:2359-70. Randomised, placebo-controlled, n = 412. PubMed 18057338
- Falutz J, et al. Effects of tesamorelin in HIV-infected patients with abdominal fat accumulation: a randomized placebo-controlled trial with a safety extension. J Acquir Immune Defic Syndr. 2010;53:311-22. n = 404. PubMed 20101189
- Falutz J, et al. Effects of tesamorelin (TH9507) in HIV-infected patients with excess abdominal fat: a pooled analysis of two multicenter, double-blind placebo-controlled phase 3 trials. J Clin Endocrinol Metab. 2010;95:4291-304. n = 806. PubMed 20554713
- Mangili A, et al. Predictors of treatment response to tesamorelin in HIV-infected patients with excess abdominal fat. PLoS One. 2015;10:e0140358. Post-hoc analysis of both phase 3 trials, sponsor-funded. PMC4601733
- Ditta AM, et al. Efficacy and safety of tesamorelin in people living with HIV with lipodystrophy: a systematic review and meta-analysis. J Int Assoc Provid AIDS Care. 2026. Four RCTs, 909 people, 16.6% women. PMC13428105
- Makimura H, et al. Metabolic effects of a growth hormone-releasing factor in obese subjects with reduced growth hormone secretion: a randomized controlled trial. J Clin Endocrinol Metab. 2012;97:4769-79. n = 60. PMC3513535
- Stanley TL, et al. Effect of tesamorelin on visceral fat and liver fat in HIV-infected patients with abdominal fat accumulation: a randomized clinical trial. JAMA. 2014;312:380-9. n = 50. PMC4363137
- Stanley TL, et al. Effects of tesamorelin on non-alcoholic fatty liver disease in HIV: a randomised, double-blind, multicentre trial. Lancet HIV. 2019;6:e821-30. n = 61. PMC6981288
- Baker LD, et al. Effects of growth hormone-releasing hormone on cognitive function in adults with mild cognitive impairment and healthy older adults. Arch Neurol. 2012;69:1420-9. Randomised, placebo-controlled, n = 152. PMC3764914
- González-Sales M, et al. Population pharmacokinetic and pharmacodynamic analysis of tesamorelin in HIV-infected patients and healthy subjects. J Pharmacokinet Pharmacodyn. 2015;42:287-99. n = 41. PubMed 25895899
- Greendale GA, et al. Changes in regional fat distribution and anthropometric measures across the menopause transition. J Clin Endocrinol Metab. 2021;106:2520-34. SWAN cohort, n = 380. PubMed 34061966
- Lovejoy JC, et al. Increased visceral fat and decreased energy expenditure during the menopausal transition. Int J Obes. 2008;32:949-58. n = 156. PubMed 18332882
- Weissberger AJ, Ho KK, Lazarus L. Contrasting effects of oral and transdermal routes of estrogen replacement therapy on 24-hour GH secretion, IGF-I and GH-binding protein in postmenopausal women. J Clin Endocrinol Metab. 1991;72:374-81. PubMed 1991807
- Wolthers T, et al. Oral estrogen antagonizes the metabolic actions of growth hormone in growth hormone-deficient women. Am J Physiol Endocrinol Metab. 2001;281:E1191-6. Crossover, n = 8. PubMed 11701433
- Phelan N, et al. Quantification of the adverse effect of ethinylestradiol containing oral contraceptive pills when used in conjunction with growth hormone replacement in routine practice. Clin Endocrinol. 2012;76:729-33. n = 88. PubMed 22098528
- ClinicalTrials.gov search for tesamorelin trials, checked November 5, 2026. ClinicalTrials.gov
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. Tesamorelin is a prescription drug approved by the FDA only for excess abdominal fat in adults with HIV-associated lipodystrophy; any other use is off-label and has not been studied in large trials in women. Do not use it if you are pregnant, and talk to your doctor about your hormones, blood sugar and cancer screening before starting.