Teriparatide is the drug that adds bone. Every other osteoporosis medicine most people have heard of slows the loss; this one, 20 micrograms under the skin once a day, grew spine density 9.7% in 19 months and cut new spine fractures from 14% to 5% in the trial that got it approved in 2002 (PMID 11346808). Twenty-four years later it is generic, its cancer warning is gone, and the fridge rule is still the thing that trips people up. This is the guide for the person who has just been prescribed it, or is deciding whether to be.
🔑 Key Takeaways
- Why a hormone that normally dissolves bone builds it when you inject it once a day, and what that means for the one dose rule.
- The 2020 label change that quietly ended the two-year limit, and the sentence that replaced it.
- What happened in the only trial that put teriparatide against a bisphosphonate head to head.
- The order of drugs that gained 6.6% at the hip over four years, and the order that lost bone.
- Why the generic pen costs more than the brand on a coupon site this month.
If a DEXA report or a fracture has put you in the high-risk group, you have probably already been through the bisphosphonate conversation. Teriparatide is the step beyond it: a daily injection, a time-limited course, and a plan for what comes after. Most of what you will find online about it is a label summary or a pharmacy price page. Below is the trial record, the current label, and the price, with every number sourced.
What teriparatide is
Teriparatide is the first 34 amino acids of human parathyroid hormone, PTH(1-34), made in bacteria by recombinant DNA. The full hormone has 84 amino acids; this fragment carries the part that acts on bone. Eli Lilly sells it as Forteo, approved November 26, 2002. Alvogen's Bonsity followed in October 2019 by the 505(b)(2) route, and true generics from Teva and Apotex were approved on November 16, 2023, with Lilly's own authorised generic (Prasco) a day later and Amphastar's in December 2025 (FDA letter, Teva ANDA). Same molecule, same 20 mcg dose, same 28-dose pen; every current label carries the same three indications. Lilly still sells Forteo in the US (its label was revised in August 2026), but it withdrew the brand from Canada on February 24, 2026 "for business reasons" (Health Canada shortage report), a reminder that the generics now carry the market.
How it builds bone when PTH normally destroys it
Chronically high parathyroid hormone, as in hyperparathyroidism, strips calcium out of the skeleton. So injecting a piece of it to build bone sounds backwards, and the explanation is timing. A brief daily pulse of PTH(1-34) activates bone-forming osteoblasts and switches off before the bone-resorbing osteoclasts catch up. A continuous signal does the opposite. Teriparatide's half-life after injection is about an hour, which is what keeps the pulse brief. That is also why the drug can only ever be a once-a-day injection, why the label says never two in one day, and why no slow-release version exists.
Who it is approved for
The label lists three groups, all defined by high fracture risk: postmenopausal women with osteoporosis who have had an osteoporotic fracture, have multiple risk factors, or have failed or cannot tolerate other therapy; men with primary or hypogonadal osteoporosis at high risk; and men and women with glucocorticoid-induced osteoporosis from sustained prednisone-equivalent doses of 5 mg a day or more (Forteo PI, section 1). Of the two anabolic injections, teriparatide is the only one with the steroid-osteoporosis indication and the only one with a fracture claim in men.
The Fracture Prevention Trial: what 1,637 women showed
The pivotal trial randomised 1,637 postmenopausal women who already had vertebral fractures to placebo, 20 mcg or 40 mcg of teriparatide daily, with calcium and vitamin D for everyone, and followed them for a median of 21 months (PMID 11346808). Lilly funded it. The trial ended early, not because the drug failed, but because bone tumours had turned up in long-term animal toxicology (the parallel men's trial reports the same reason, PMID 12510800).
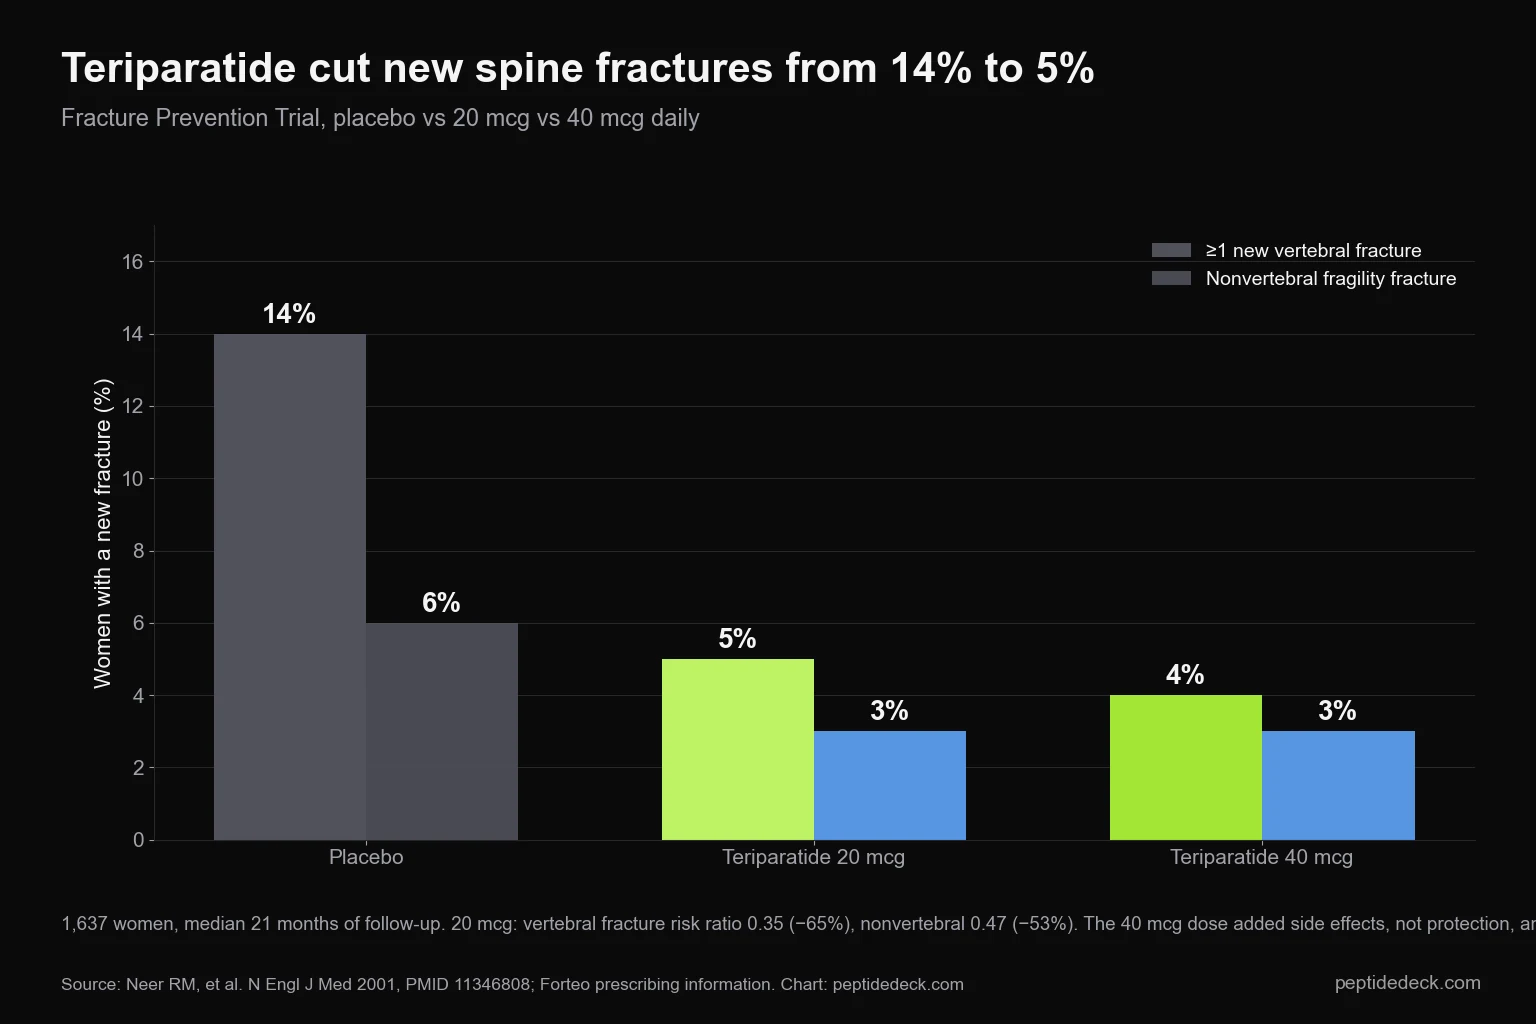
New vertebral fractures: 14% on placebo, 5% on 20 mcg, 4% on 40 mcg, a 65% relative reduction at the approved dose. Nonvertebral fragility fractures: 6% against 3%, a 53% reduction on the label's count. The 40 mcg dose bought no extra fracture protection and more side effects, which is why 20 mcg became the dose.
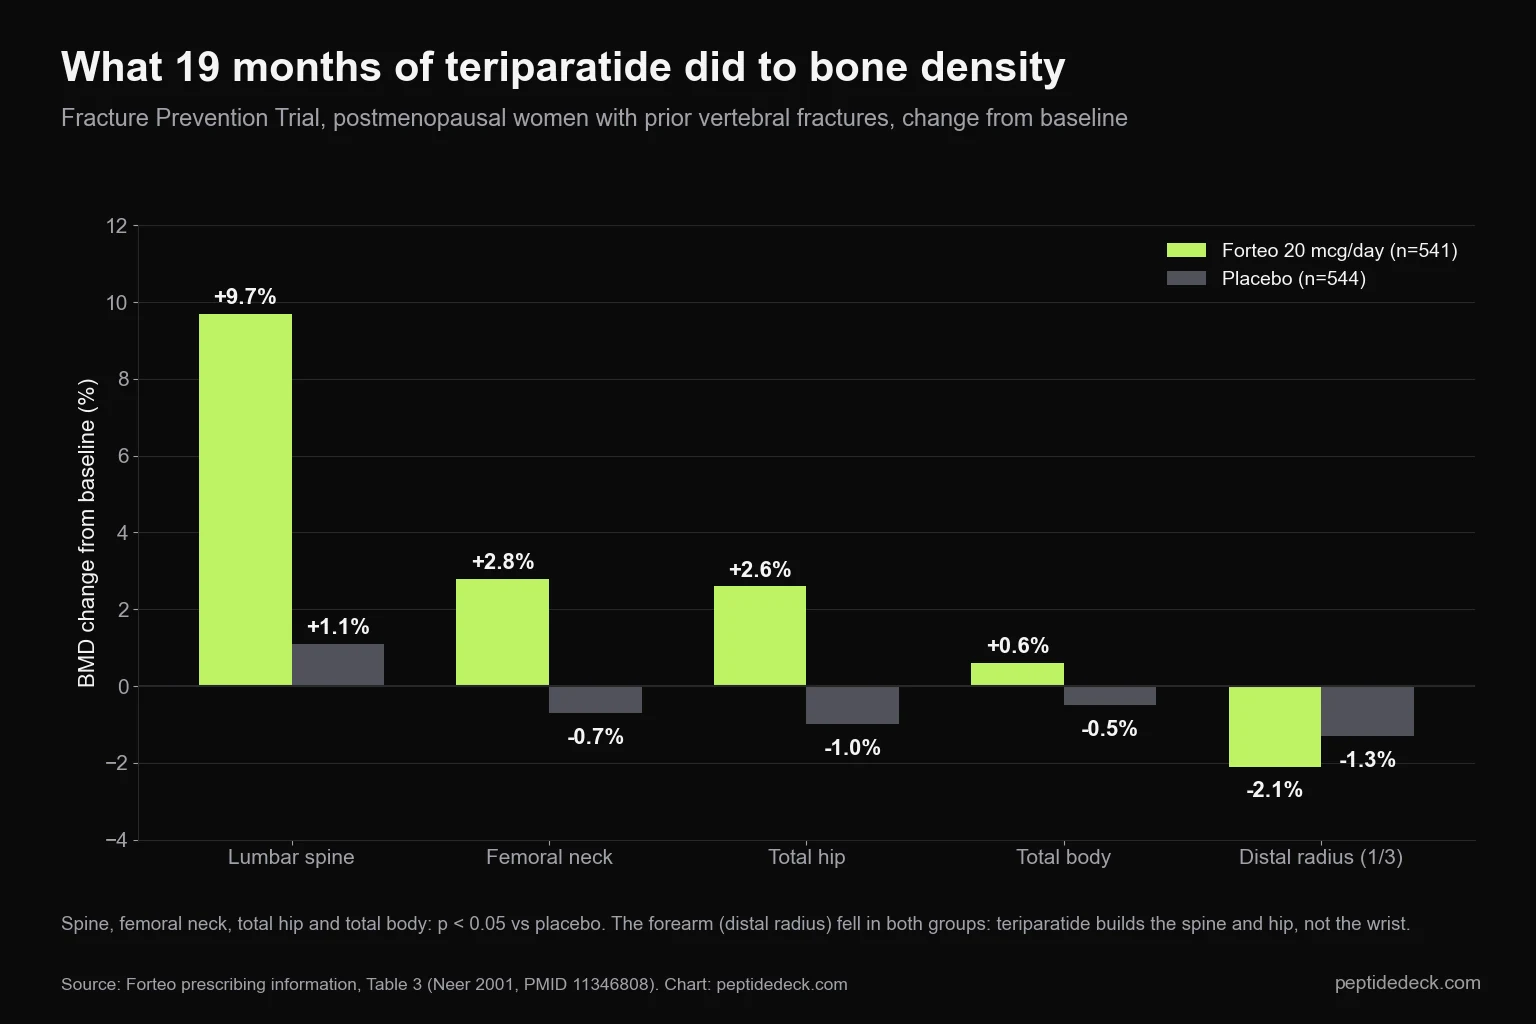
Density tells the same story with one footnote. Spine +9.7% against +1.1%, femoral neck +2.8% against a 0.7% loss, total hip +2.6% against a 1.0% loss. The forearm fell in both groups, slightly more on teriparatide (Forteo PI, Table 3). Teriparatide builds the spine and hip, the sites that break with the worst consequences; it does nothing for the wrist.
Teriparatide vs a bisphosphonate: the VERO trial
The question most patients actually face is "why not the tablet", and one trial answered it directly. VERO randomised 1,360 postmenopausal women with severe osteoporosis to daily teriparatide or weekly risedronate for 24 months, double-dummy so nobody knew which they had (PMID 29129436). New vertebral fractures: 5.4% against 12.0%. Clinical fractures: 4.8% against 9.8%. Nonvertebral fragility fractures: 4.0% against 6.1%, which did not reach significance.
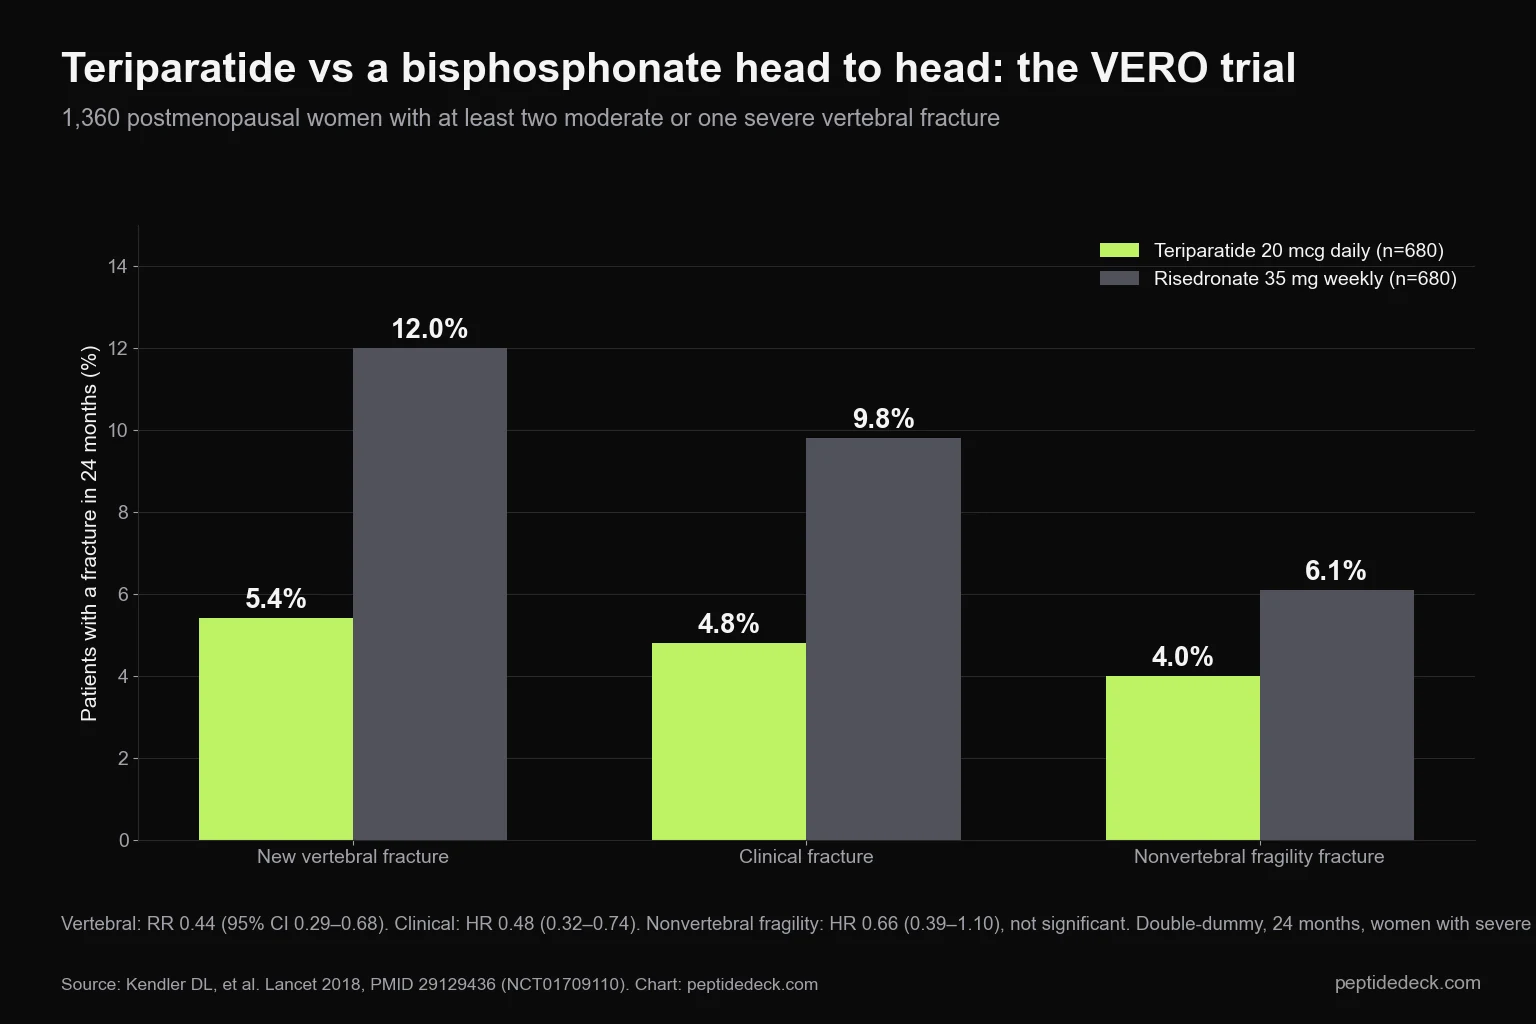
That is the evidence behind the guideline position: in people at very high risk, the anabolic goes first. It is also why the drug is reserved. For most people with moderate risk a bisphosphonate is still the right first step, because it is cheap, oral and backed by decades of fracture data.
Dose, injection and the pen
The dose is 20 mcg once a day under the skin of the thigh or abdomen. The pen contains 560 mcg in 2.24 mL, enough for 28 daily doses; needles are sold separately. Keep it in the fridge at 2 to 8 °C at all times except while injecting, recap it after each dose, never freeze it or use it if it has been frozen, and throw it away 28 days after the first dose even if drug is left (Forteo PI, sections 2 and 16). Unlike the abaloparatide pen, there is no room-temperature allowance at all.

Three rules from the label. Take the first several doses where you can sit or lie down, because blood pressure can drop on standing within four hours; it happened to about 5% of healthy volunteers and passed without treatment. Never inject twice in one day; that is the label's only missed-dose rule, so if you skip a day, resume the next day rather than doubling. And take calcium and vitamin D if your diet is short, which in the trials meant 1,000 mg and at least 400 IU a day.

Side effects: the label table, not the forum version
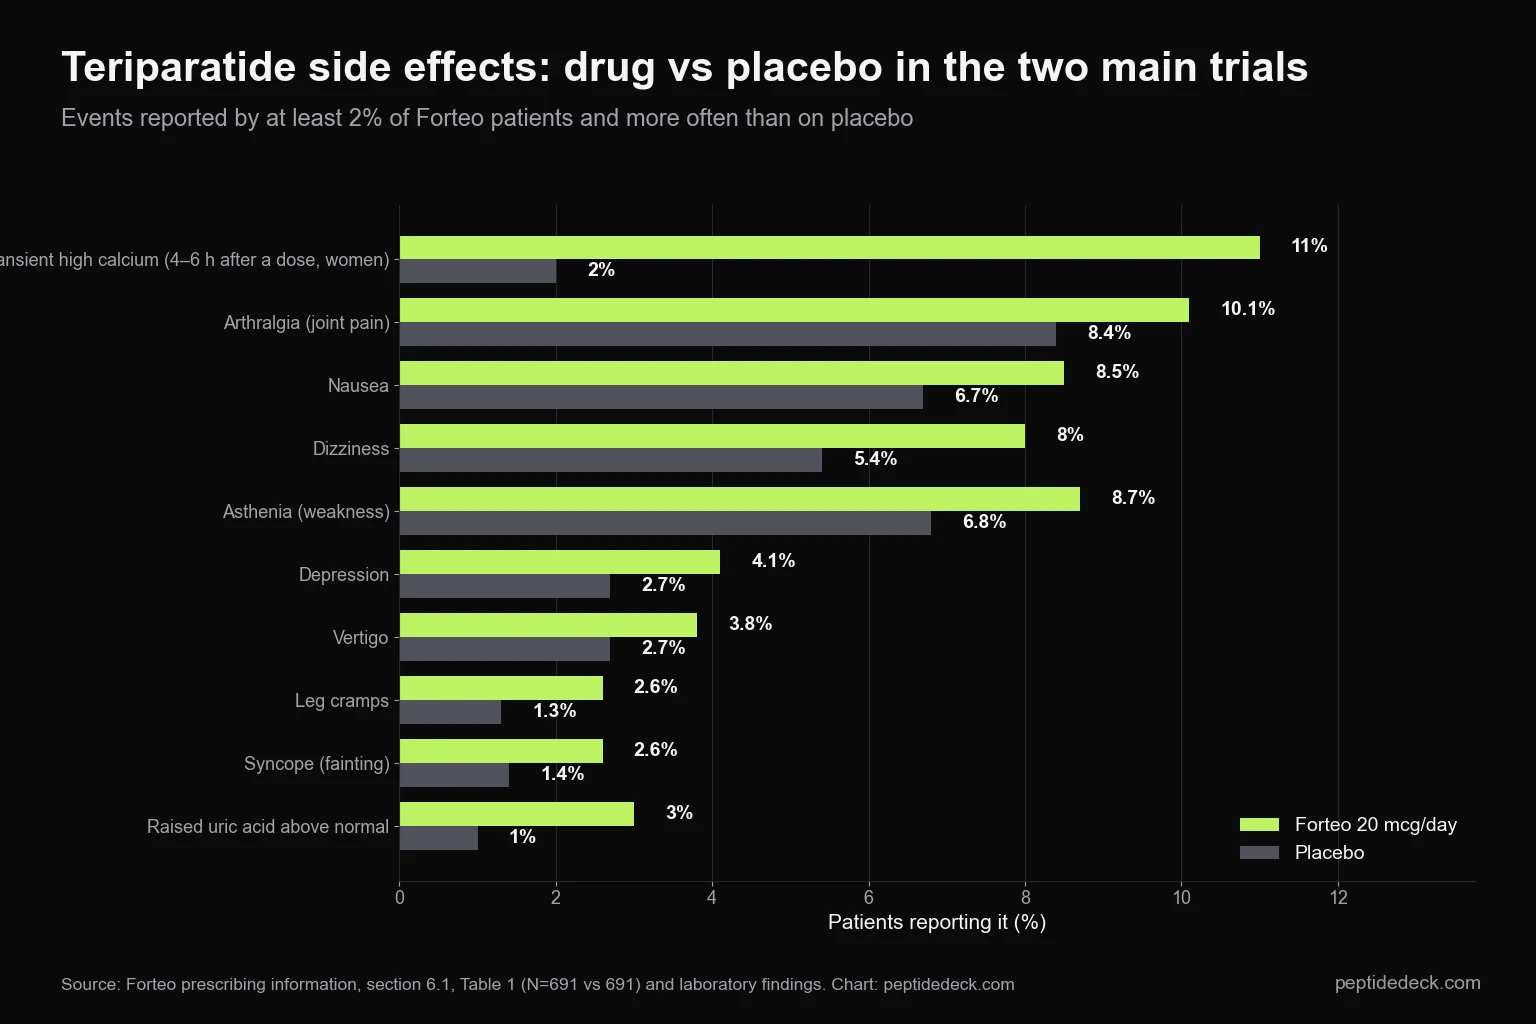
In the two principal trials the differences from placebo were small. Joint pain 10.1% against 8.4%, nausea 8.5% against 6.7%, dizziness 8.0% against 5.4%, leg cramps 2.6% against 1.3%, fainting 2.6% against 1.4% (Forteo PI, Table 1). The one that matters medically is calcium: at least one high blood calcium reading 4 to 6 hours after a dose occurred in 11% of women and 6% of men against 2% and 0% on placebo, confirmed on a repeat reading in 3% of women, and the peak stayed under 11 mg/dL in more than 99% of them. Uric acid went above normal in 3% against 1% without more gout or kidney stones. Antibodies to the drug appeared in 3% of women after about a year with no effect on efficacy.
Two interactions and exclusions to know. High calcium can make digoxin toxic, so anyone on digoxin should know the signs. Teriparatide should not be used by anyone at higher baseline risk of osteosarcoma (open growth plates, Paget's disease or other metabolic bone disease, bone metastases or a history of skeletal cancer, prior radiation involving the skeleton, hereditary osteosarcoma syndromes), by anyone with a hypercalcaemic disorder such as primary hyperparathyroidism, and only with care in active kidney stones. The one formal contraindication is a history of severe allergic reaction to it.

The osteosarcoma warning, and what the 2020 change did and did not say
For 18 years Forteo carried a boxed warning. Laboratory animals given 3 to 60 times the human exposure for most of their lives developed osteosarcoma, dependent on dose and duration (2002 label). The FDA's answer was the box plus a two-year lifetime cap. Then the surveillance came in: a 15-year US registry study of adult osteosarcoma found three cases with prior teriparatide where 4.17 were expected, a standardised incidence ratio of 0.72 (PMID 32990990), and two claims databases found 3 and 0 cases among 379,283 and 153,316 users.

On November 16, 2020 the FDA approved supplement S-054: the boxed warning came off and section 2.3 was rewritten (FDA approval letter). What the label now says is precise, and worth quoting: "an increased risk of osteosarcoma has not been observed in observational studies in humans. There are limited data assessing the risk of osteosarcoma beyond 2 years." It did not declare the risk zero, and it kept the exclusion list above.
How long you can take it: the two-year rule, rewritten
Before 2020 the label said use beyond two years in a lifetime was not recommended. The current wording is: "Use of FORTEO for more than 2 years during a patient's lifetime should only be considered if a patient remains at or has returned to having a high risk for fracture" (Forteo PI, section 2.3). Two years is still the default course, and the Endocrine Society guideline recommends teriparatide or abaloparatide "for up to two years" in very-high-risk women (Endocrine Society 2019). The difference is that a second course, or a longer one, is now a clinical decision rather than a label violation. Abaloparatide's label was not changed the same way; see our abaloparatide guide.
What comes after: the sequence that keeps the bone
Bone built on teriparatide is lost again if nothing follows it. The Endocrine Society's recommendation is explicit: after a course of teriparatide or abaloparatide, treat with an antiresorptive "to maintain bone density gains" (rec. 4.2). The clearest data on the order come from DATA-Switch, which gave 2 years of teriparatide then 2 years of denosumab, or the reverse (PMID 26144908).
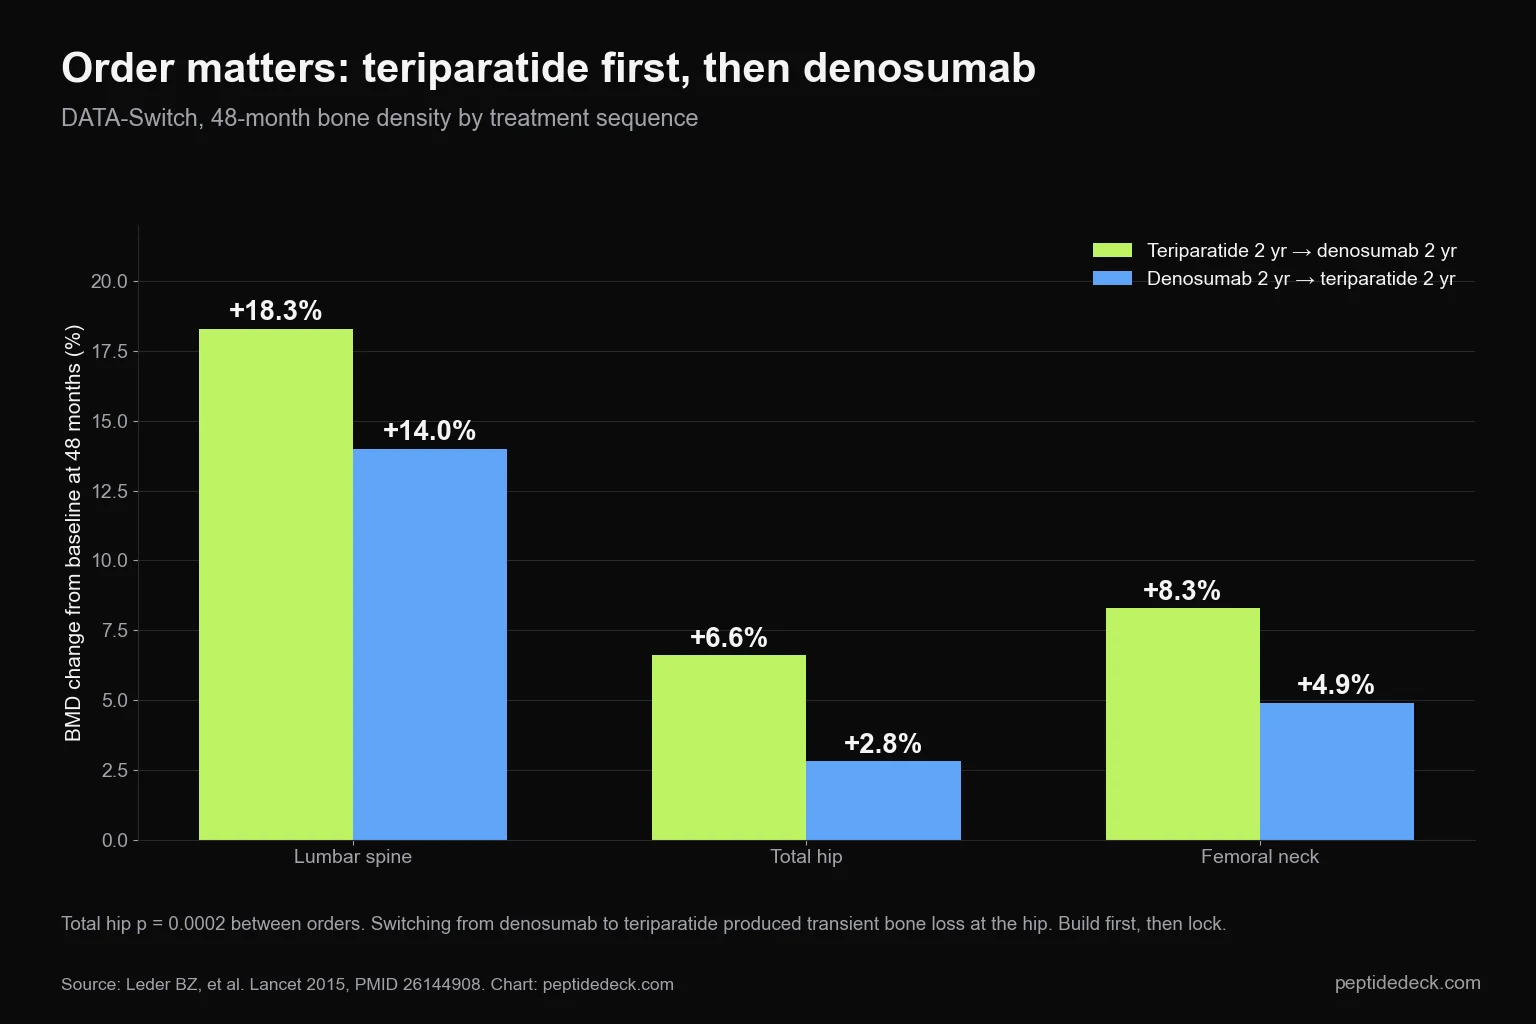
Teriparatide first, then denosumab: +18.3% at the spine and +6.6% at the total hip over four years. The other way round: +14.0% and +2.8%, with a transient loss at the hip when teriparatide followed denosumab. The older PaTH study found the same with the full hormone and alendronate, and that the group given placebo after PTH "lost substantial bone mineral density" (PMID 16093464). The practical rule: have the follow-on prescription in hand before the last pen runs out, and if you are already on denosumab, the switch to teriparatide needs an overlap plan from your prescriber, not a gap.
What teriparatide costs in 2026
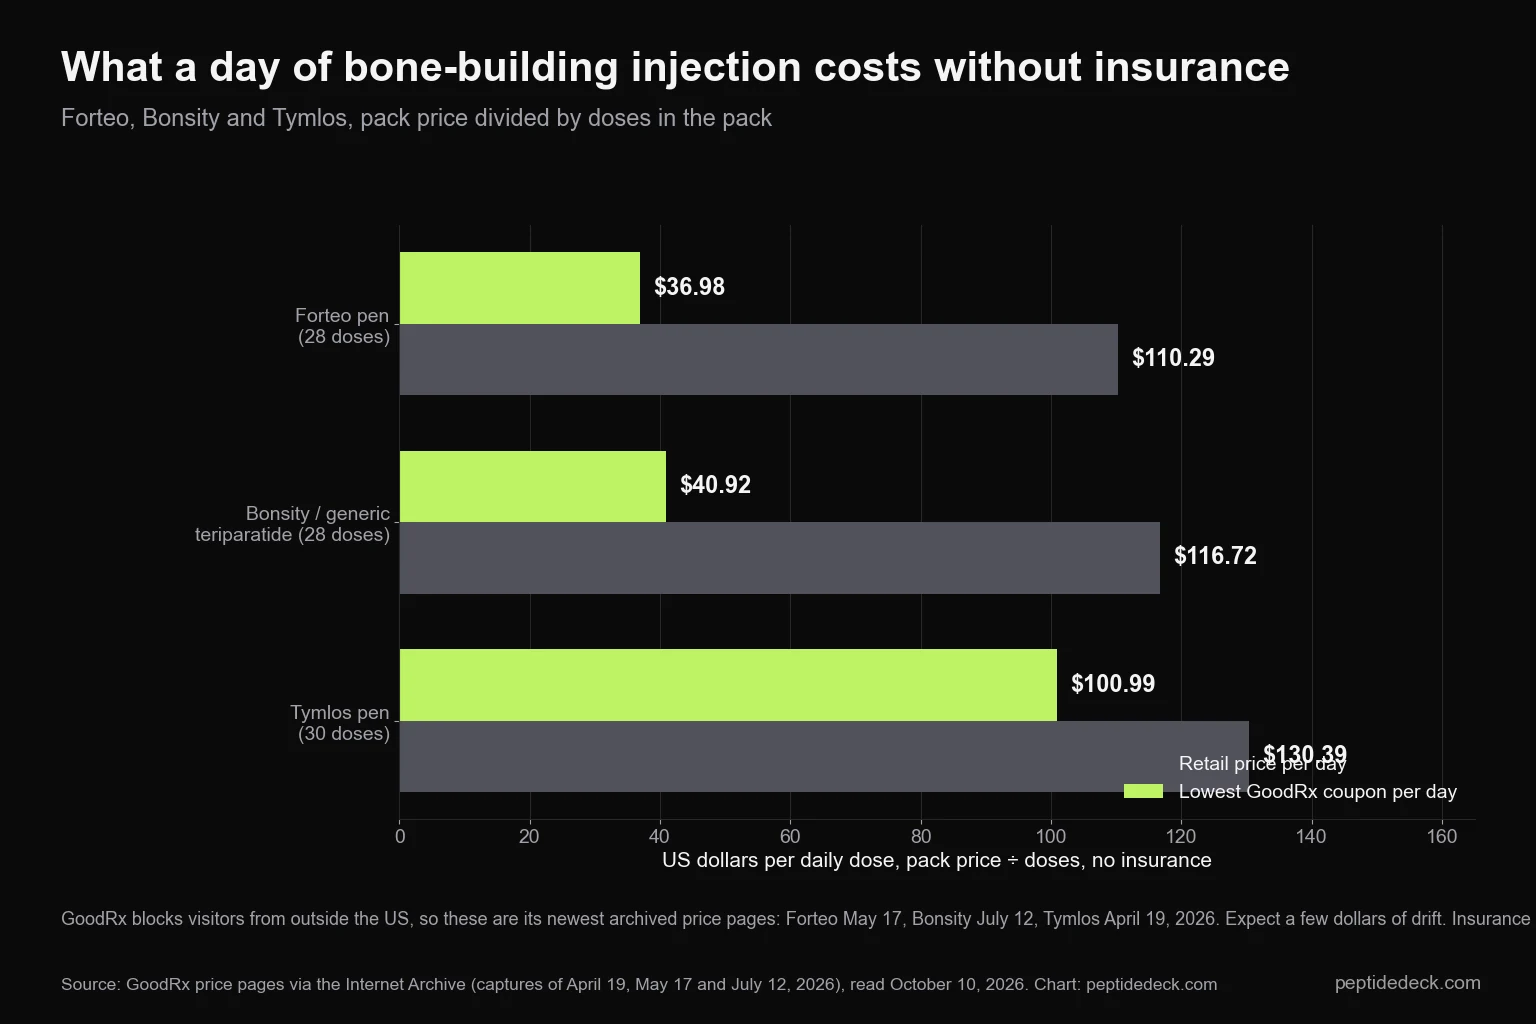
The price has fallen, and not quite how you would expect. GoodRx blocks visitors from outside the US, so we read its newest archived price pages: the May 17, 2026 capture lists the Forteo pen at $1,035.37 with a coupon against $3,088.14 retail, and the July 12, 2026 capture lists Bonsity at $1,145.82 against $3,268.05 (GoodRx, Forteo capture; GoodRx, Bonsity capture). Per daily dose that is $36.98 for the brand and $40.92 for the 505(b)(2) generic: on these pages the generic did not undercut the brand, because the Lilly coupon price on Forteo sits below it. Expect a few dollars of drift by the time you read this. Lilly's own list price page was behind a bot check when we checked.
Insurance is where the real price is set. Lilly's Forteo Savings Card lets commercially insured patients "pay as little as $4 per month", capped at $10,600 of savings and 13 fills per calendar year, with a month defined as 28 days; it excludes Medicare, Medicaid, TRICARE, VA and other government coverage, and the current card expires December 31, 2026 (forteo.lilly.com). Uninsured and Medicare Part D patients can apply to Lilly Cares, which lists Forteo and supplies it free for up to 12 months to households under its income limits (lillycares.com). On Part D itself, the annual out-of-pocket cap is $2,100 in 2026 and rises to $2,400 in 2027, so a year of brand or generic teriparatide on a Part D plan that covers it cannot cost a patient more than that at the pharmacy counter (CMS, CY 2026 Part D).
Prior authorisation is standard, and the criteria are public. Mass General Brigham Health Plan's commercial policy, effective July 1, 2026, approves teriparatide for 12 months with a T-score of −2.5 or lower plus a low-trauma fracture of the hip, spine, humerus, pelvis or forearm, or plus failure of one osteoporosis drug; with a T-score between −1.0 and −2.5 plus a fracture, or plus a failed drug and a FRAX risk of 20% or more; or with any fragility fracture regardless of bone density. It allows one pen per 28 days and a second year only if risk is still high (MGB policy PDF). Other payers' wording varies, the shape does not. Ask the prescriber's office to attach the DEXA report and fracture history; a missing document is the usual reason for a denial. For the price of the other anabolic pen and how the two compare, our abaloparatide guide has the same table.
Teriparatide vs abaloparatide, romosozumab and bisphosphonates
Head to head on bone density in ACTIVE, teriparatide gained 9.1% at the spine, 2.8% at the total hip and 2.3% at the femoral neck in 18 months, against 9.2%, 3.4% and 2.9% for abaloparatide; the hip difference was statistically real, the fracture difference was not (NCT01343004 results). Teriparatide caused high blood calcium about twice as often (6.4% vs 3.4%). What it has that abaloparatide does not: a generic, the glucocorticoid indication, a fracture claim in men, and a label that permits more than two years. An oral teriparatide tablet, EB613, is due to start Phase 3 in late 2026. For how all of these rank against the peptides sold for bone without a prescription, see our guide to peptides for osteoporosis.
Sticking with a daily injection
About six in ten people are still injecting at one year. In a US claims analysis, 12-month persistence with teriparatide was 59.1%, better than oral bisphosphonates (29 to 35%) and below denosumab (68.3%) (PMID 26308229). The gap between people who finish the course and people who do not is mostly logistics: the fridge, the refill timing, the copay. Set a daily alarm, keep the next pen in the fridge before the current one runs out, and treat the follow-on drug as part of the course rather than a separate decision.
What to ask your doctor
- Does my fracture risk put me in the group where an anabolic comes first, or is a bisphosphonate the right start?
- Brand or generic: which does my plan cover, and does the savings card apply to me?
- Which drug follows the course, and when should that prescription be written?
- Do I need a blood calcium check, and does my digoxin, kidney stone or hyperparathyroidism history change the plan?
- Do not stop a prescribed osteoporosis drug because of something you read online, including this page.
Frequently Asked Questions
Sources
- Neer RM, et al. Effect of parathyroid hormone (1-34) on fractures and bone mineral density in postmenopausal women with osteoporosis. N Engl J Med. 2001;344:1434-1441. PMID 11346808
- Orwoll ES, et al. The effect of teriparatide therapy on bone density in men with osteoporosis. J Bone Miner Res. 2003;18:9-17. PMID 12510800
- Kendler DL, et al. Effects of teriparatide and risedronate on new fractures in post-menopausal women with severe osteoporosis (VERO). Lancet. 2018;391:230-240. PMID 29129436
- Leder BZ, et al. Denosumab and teriparatide transitions in postmenopausal osteoporosis (the DATA-Switch study). Lancet. 2015;386:1147-1155. PMID 26144908
- Black DM, et al. One year of alendronate after one year of parathyroid hormone (1-84) for osteoporosis. N Engl J Med. 2005;353:555-565. PMID 16093464
- Miller PD, et al. ACTIVE trial. JAMA. 2016;316:722-733. PMID 27533157; posted results NCT01343004
- Gilsenan A, et al. Teriparatide did not increase adult osteosarcoma incidence in a 15-year US postmarketing surveillance study. J Bone Miner Res. 2021;36:244-251. PMID 32990990
- Cosman F, et al. Romosozumab treatment in postmenopausal women with osteoporosis (FRAME). N Engl J Med. 2016;375:1532-1543. PMID 27641143
- Black DM, et al. Randomised trial of effect of alendronate on risk of fracture in women with existing vertebral fractures (FIT). Lancet. 1996;348:1535-1541. PMID 8950879
- Cheng LI, et al. Persistence and compliance with osteoporosis therapies among women in a commercially insured population in the United States. J Manag Care Spec Pharm. 2015;21:824-833. PMID 26308229
- Forteo (teriparatide injection) prescribing information, revised August 2026 (S-059). accessdata.fda.gov
- Forteo prescribing information, 2002 original label with boxed warning. accessdata.fda.gov
- FDA approval letter, NDA 021318/S-054, November 16, 2020: removal of the boxed warning and treatment-duration change. accessdata.fda.gov
- FDA approval letters: Bonsity NDA 211939 (October 4, 2019) letter; Teva ANDA 208569 (November 16, 2023) letter
- Eastell R, et al. Pharmacological management of osteoporosis in postmenopausal women: an Endocrine Society clinical practice guideline. 2019. endocrine.org
- Eli Lilly. Colorado wholesale acquisition cost disclosure, Forteo 560 mcg/2.24 mL, $4,289.89, accessed October 2025. pricinginfo.lilly.com
- Mass General Brigham Health Plan. Parathyroid hormone analogs prior authorization policy, commercial and exchange, effective July 1, 2026. policy PDF
- GoodRx price pages for Forteo (May 17, 2026 capture) and Bonsity (July 12, 2026 capture), Internet Archive; GoodRx is not reachable from outside the US. forteo · bonsity
- Lilly. Forteo Savings Card terms, read October 10, 2026. forteo.lilly.com · Lilly Cares available medications. lillycares.com · CMS fact sheet, Final CY 2026 Part D redesign program instructions. cms.gov
Medical Disclaimer: This article is for educational purposes only and is not medical advice. Teriparatide is a prescription medicine that requires a diagnosis, a fracture-risk assessment and monitoring by a qualified clinician. Do not start, stop or change any osteoporosis treatment because of this page.